
Aesthetic and functional restorations are planned with composite bonding, teeth whitening and minimally invasive smile design while preserving natural tooth tissue.
Restorative and Aesthetic Dentistry
Restorative and aesthetic dentistry aims to improve teeth affected by decay, fracture or discoloration both functionally and visually.
In composite bonding and filling procedures, preserving as much tooth tissue as possible is the basis of the minimally invasive principle.
Teeth whitening may be planned with in-office, at-home or combined protocols; sensitivity and colour stability vary from person to person.
In smile design, facial proportions, the lip line and the tooth-gum relationship are assessed together; a digital mock-up may provide a preview.
Adhesive techniques and shade layering may help create a natural appearance in aesthetic composite restorations.
Closing diastemas between front teeth may be approached with composite or porcelain laminate options.
For worn or fractured teeth, direct composite restoration, crowns or veneer combinations may be suggested according to the clinical situation.
Aesthetic renewal of old amalgam or composite fillings may also be considered for functional reasons if leakage or fracture is suspected.
In fluorosis, tetracycline staining or age-related colour change, whitening depth depends on the type of lesion.
For fractured front teeth after trauma, emergency bonding or covering restorations may provide temporary or definitive solutions.
In the posterior region, composite onlay and inlay restorations may be considered as alternatives to amalgam.
Unnecessary removal of sound tooth tissue is avoided; preparation limits are determined by restoration type and decay extension.
Adhesive dentistry techniques may contribute to the longevity of composite and porcelain restorations; technical precision is important.
Occlusal contacts and anterior guidance planning may be adjusted after treatment to preserve chewing function.
Photographic records and shade-tab matching help maintain consistency in aesthetic outcomes.
Preventive measures may be applied before restoration in patients with high caries risk.
Rubber dam isolation may improve bond quality by preventing contamination during adhesive restorations.
At the first examination, oral hygiene, gum health and caries screening are assessed; active periodontal disease may be treated first.
The patient’s expectations are compared with realistic goals; digital smile design or wax-up simulation may be offered.
Restoration material is selected by balancing durability, aesthetics and cost.
Treatment stages and the number of appointments vary according to the planned procedures; temporary restorations may be used in the interim.
Occlusion analysis and TMJ assessment may be included in comprehensive aesthetic cases.
Smile design software may strengthen expectation alignment by providing visual simulation before patient approval.
Composite surfaces may discolour or wear over time; regular check-ups and polishing are recommended.
After whitening, avoiding certain foods and drinks may be recommended for colour stabilisation; the duration is individual.
When night bruxism is present, a protective splint may extend the life of restorations.
Annual dental check-ups support monitoring of restoration integrity, marginal fit and gum health.
Restorative procedures do not carry a lifetime guarantee; maintenance and regular follow-up affect the result.
Early intervention in colour change or marginal staining may help extend restoration life.
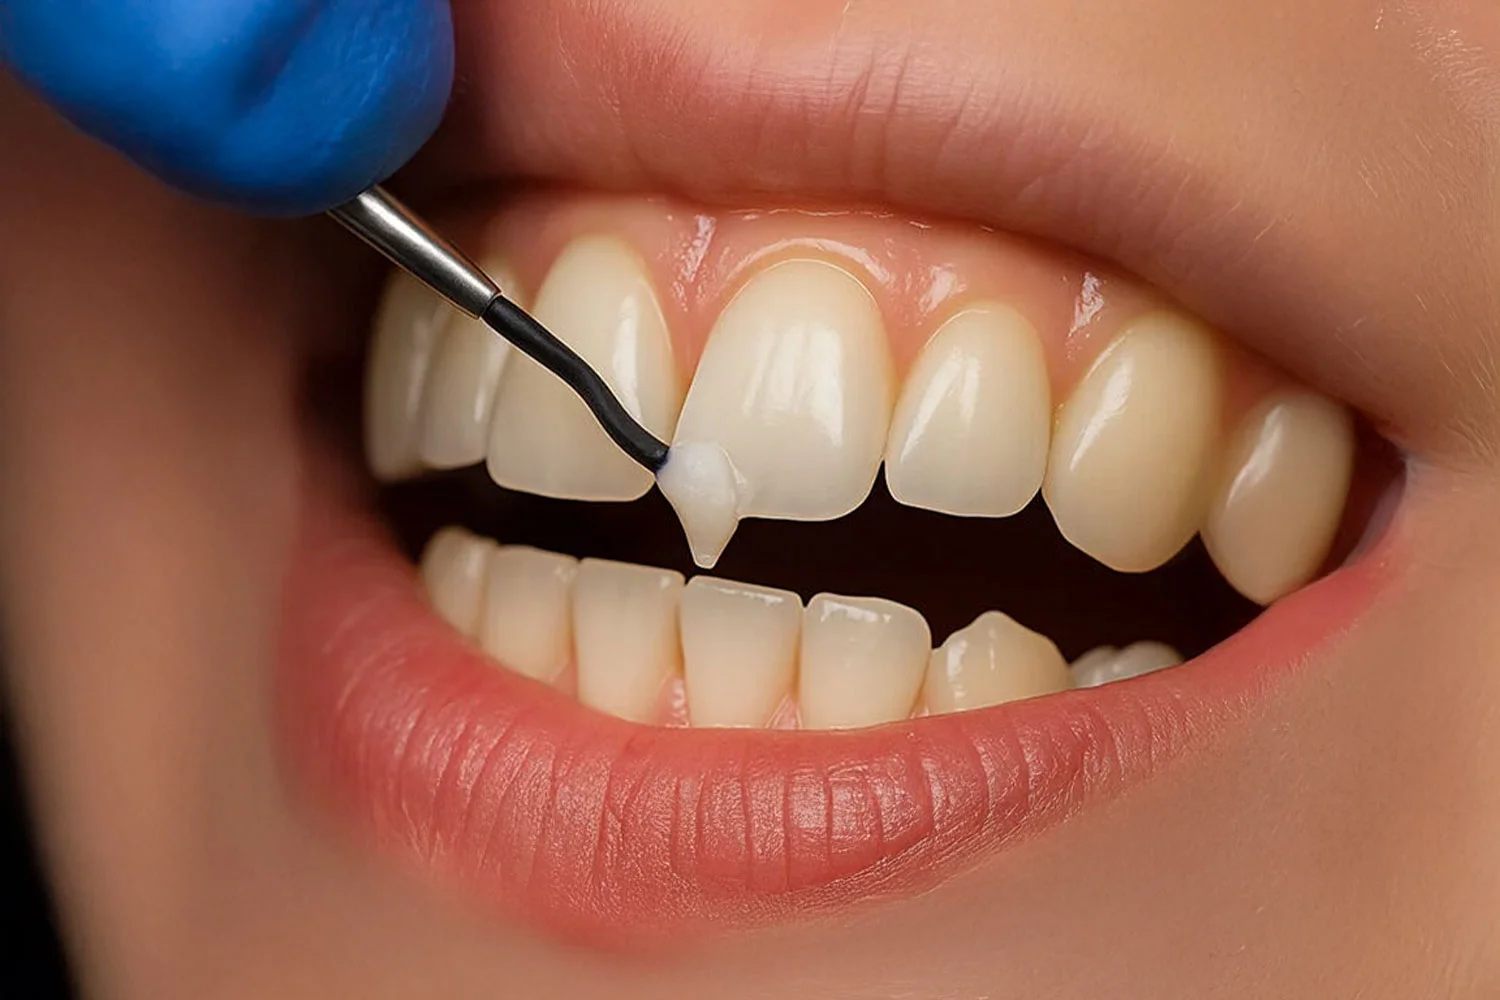
A minimally invasive aesthetic procedure in which shape, size and surface aesthetics of front teeth are adjusted directly in the clinic with tooth-coloured composite material.
Read more
A composite filling is a direct repair of tooth tissue lost to decay or damage, using a tooth-coloured composite material. Suitability is based on the amount of lost tissue, the condition of the tooth and chewing load.
Read more
Teeth whitening lightens the colour of natural teeth. Suitability is based on tooth and gum health, the cause of discolouration and existing restorations. Fillings, veneers and crowns do not whiten like natural teeth.
Read more
A restorative approach in which smile aesthetics are planned with composite bonding, whitening and minimally invasive adjustments; it is not focused on prosthetic veneers.
Read more
The cause of a tooth gap (diastema) is assessed at examination. Bonding, orthodontics, or porcelain laminate in selected cases are planned individually; not every gap needs to be closed.
Read more
Aesthetic-functional restorative repair planned after assessing the cause, bite relationships and remaining tissue in chipped or worn teeth; it is not only cosmetic.
Read more
Imaging assessment and consultation that support treatment planning with panoramic X-rays and Cone Beam CT (CBCT).
Read more
A planned and safety-focused treatment approach for surgical procedures such as dental implants, All-on-4, All-on-6, impacted wisdom-tooth removal, bone grafting and sinus lift.
Read more
Material selection and functional-aesthetic solutions for laminate veneers, zirconia crowns, E-max, implant-supported prostheses and full-mouth rehabilitation. A plan is created after examination.
Read more
Gum disease care, aesthetic gum adjustments, Gummy Smile management and supportive periodontal treatments; regular maintenance remains important.
Read more
Endodontic options focused on keeping the natural tooth, including root canal treatment, periapical lesion management and root canal retreatment. A plan is made after examination.
Read more
Aesthetic and functional management of crowding and bite irregularities with braces, clear aligners and retention treatments. A plan is made after examination.
Read more
Paediatric dentistry covers examination, prevention and treatment to protect primary and permanent teeth. The plan is based on the child’s age, tooth condition and individual needs.
Read more





